Contraception

This page reviews every method of contraception, from the most reversible to the most permanent, and gives for each its real-world effectiveness rather than the theoretical figure.

Illustration: Contraception

Appear on this page

Get our daily news watch

What is the same everywhere

The medicine does not change across borders. Hormonal methods — pill, patch, ring, implant, injection — are highly effective when used correctly. The intrauterine device is among the most reliable and cheapest long-term options precisely because it needs no daily action. And only condoms protect against sexually transmitted infections as well as pregnancy; no hormonal method does.

Which contraception suits me?

Eight questions, one minute, and a pointer: the methods that fit your situation, and those that cannot. Take the test →

What differs: prescription, price, age

Midwife presenting the different contraceptive methods on a tray to a young woman

Three things determine real access. First, prescription rules: hormonal methods almost everywhere require one, while emergency contraception is increasingly available over the counter. Second, cost, ranging from full public funding through age-limited schemes to full self-payment. Third, the rules for minors: some systems guarantee confidentiality explicitly, others require a parent's involvement.

Effectiveness compared

Two columns, and it is the gap between them that matters. Perfect use measures the method under ideal conditions; typical use measures what actually happens, missed doses and mistakes included.

MethodPerfect useTypical use
Implant0.10.1
Vasectomy0.10.15
Hormonal IUD0.1 to 0.40.1 to 0.4
Tubal sterilisation0.50.5
Copper IUD0.60.8
Three-monthly injection0.24
Symptothermal method0.42 and above
Pill, patch, ring0.37
External condom213
Standard Days Method512
Mucus observation311 to 23
Internal condom521
Diaphragm with spermicide1617
Withdrawal422
Spermicides alone1621
Rhythm method525
No method8585

Pregnancies per 100 women during the first year of use. International reference figures, rounded.

Hormonal methods

MethodHow it worksKey points
PillBlocks ovulation (combined) or thickens cervical mucus (progestogen-only)Daily; highly effective if taken consistently; on prescription
ImplantSubdermal rod releasing a progestogenSeveral years, inserted and removed by a clinician, quickly reversible
PatchHormones through the skinChanged weekly, three weeks in four
Vaginal ringLocal hormone releaseIn for three weeks, out for one
InjectionDepot progestogenOne injection every three months; delayed return of fertility

Intrauterine devices

TypeHow it worksDuration
Copper IUDLocally toxic to sperm, hormone-free5 to 10 years depending on the model
Hormonal IUDLocal progestogen release, also reduces heavy periods3 to 8 years depending on the model
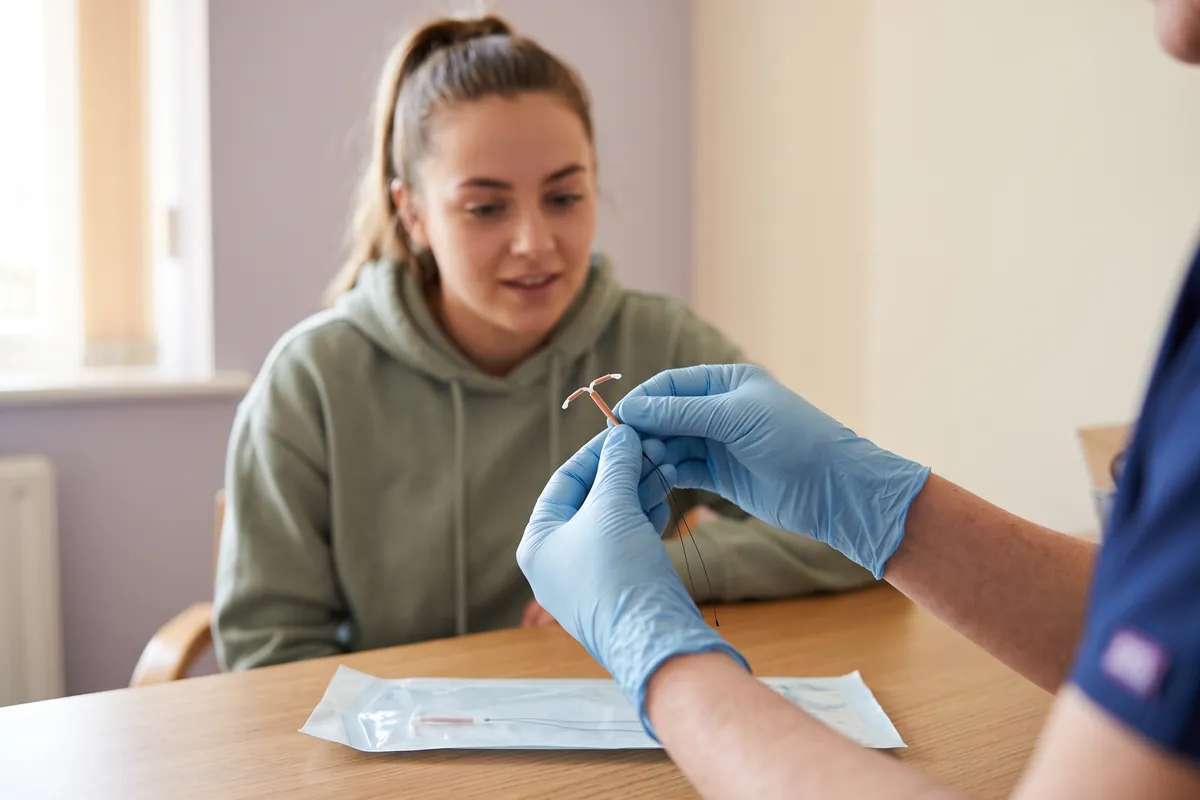
Small T-shaped copper IUD held between two gloved fingers, an attentive young woman blurred in the background
A small T-shaped copper IUD held between two gloved fingers, watched attentively by a young woman. Contrary to a stubborn misconception, it can be fitted in a woman who has never had children: this is no longer a contraindication. The copper version works without hormones, for 5 to 10 years depending on the model.

Contrary to a stubborn myth, an IUD can be fitted in a woman who has never given birth or never had penetrative sex: that is no longer a contraindication in current practice.

Barrier methods

MethodSTI protectionKey points
External condomYesSingle use, the only method available with no appointment or prescription
Internal condomYesPlaced in the vagina, up to eight hours before
Diaphragm / capNoUsed with a spermicide, with clinical support
SpermicidesNoModest effectiveness alone; a supplement to another method

Natural methods: how they actually work

Also called fertility-awareness methods, they all rest on one fact: a cycle contains only about six fertile days. Two durations explain it.

Woman still in bed taking her temperature on waking, a notebook and pencil on the bedside table

So the fertile window covers the five days before ovulation and the day itself. That leaves the real difficulty: ovulation does not fall on a fixed day. The second half of the cycle runs fairly consistently at 12 to 16 days, but the first half varies widely — stress, illness, travel or a change of routine can shift it by several days. That is what separates the methods that calculate from those that observe.

The three bodily signs

SignWhat it saysWhat it does not say
Cervical mucus That the fertile window is opening: it turns clear, stretchy and slippery, and lets sperm survive for days Exactly when it closes
Waking temperature That ovulation has happened: progesterone lifts basal temperature by 0.2 to 0.5 °C, and keeps it there That it is approaching — the signal always arrives afterwards
Cervix position A supporting sign: it becomes high, soft and open as ovulation nears Anything reliable on its own

Hence the hierarchy among natural methods. Those using the calendar alone predict an unpredictable event. Those using a single sign cover one end of the window and not the other. Those that cross mucus and temperature — the symptothermal method — bracket the window from both sides, which is why their effectiveness is of an entirely different order.

What they all require

Finally, no natural method protects against a sexually transmitted infection, and none removes the need for emergency contraception if there is doubt.

Emergency contraception: earlier is better

It works by delaying ovulation and is not an abortion. Its effectiveness falls with every hour, so the timing matters more than the choice of product. In a growing number of countries it is available without prescription, sometimes including for minors. Ask the pharmacy what is available the same day rather than waiting for an appointment.

Permanent contraception

A man in his forties listens closely to a female doctor during a calm consultation

Sterilisation is open to adults in a growing number of countries, often with no condition as to age, number of children or family situation — contrary to a widespread myth. Where it is allowed, a waiting period is generally imposed between the first consultation and the procedure, and a spouse's consent is not required. It should be treated as permanent: tubal ligation or removal in women, vasectomy in men. Reversal surgery exists but its outcome is never guaranteed.

Clinics and family planning services are usually the best entry point

Where family planning or sexual health services exist, they are typically free, confidential and quicker to reach than a specialist appointment — including for young people. They also know the local funding rules, which change often and are rarely well documented anywhere you could look them up.

The mistake that costs the most

Distance and running out of supplies cause more unintended pregnancies than method failure does. If you live far from a clinic or travel often, ask specifically about a long-acting method that works for years without resupply.


One page per method

Each method has its own page: the mechanism in detail, how to use it, effectiveness in figures, the effects to know about and what to do when something does not go to plan.

Fertility-awareness methods

The symptothermal method

Crossing temperature and mucus: the most reliable natural method, and the most demanding.

The temperature method

What basal temperature measures, how to take it, and the three-day rule.

Cervical mucus

The only sign that warns before ovulation: the pattern, the observation, the peak day.

Calendar methods

Rhythm and Standard Days: the calculation, its conditions, and why it is fragile.

Withdrawal

Neither useless nor reliable: real effectiveness, pre-ejaculate, and when it makes sense.

Breastfeeding (LAM)

Three conditions at once, six months at most, and the trap of the first period.

Cycle-tracking apps

Tracker or medical device: two very different things, routinely confused.

Hormonal, intrauterine and barrier methods

The pill

Combined or progestogen-only, missed-pill rules, contraindications and interactions.

The implant

Years with nothing to do — and the bleeding pattern to know about before insertion.

The patch and the ring

A combined pill without the daily constraint: how to use them, and how to catch up.

The injection

Every three months, discreet — but impossible to stop once given.

The IUD

Copper or hormonal, insertion and its pain, the real risks and the myths.

Condoms

The only method covering pregnancy and infection: the usage errors that cost most.

Diaphragm and spermicides

Local hormone-free methods, and the nonoxynol-9 warning.

Sterilisation

Vasectomy and tubal: two very unequal procedures, and the question of regret.

Emergency contraception

What to do after unprotected sex or a missed pill, and how quickly it has to happen.

Smoking and the combined pill: an association not to be shrugged off

After 35, smoking and the combined pill do not go together

Combined contraceptives — the combined pill, the patch, the ring — modestly raise the risk of venous thrombosis and, more rarely, of arterial events. Tobacco acts on the same mechanisms by another route: it damages the vessel wall and promotes clotting. The two do not add up, they multiply. International guidance therefore advises firmly against combined contraception for a woman aged 35 or over who smokes fifteen cigarettes a day or more, and counsels caution for any smoker over 35 whatever the amount.

The risk is heart attack and stroke — rare at that age but serious. It adds to the risk created by hypertension, diabetes, migraine with aura — which on its own contraindicates combined contraception — and a family history of thrombosis.

This is not a dead end: oestrogen-free methods do not carry the problem. The progestogen-only pill, the implant, the hormonal coil and the copper coil remain usable by a smoker over 35, with equal effectiveness — better, in fact, for the long-acting methods, which do not depend on remembering.

Quitting is not the only option — changing contraception is another, and often the simpler one in the short term. But if stopping is on the table, the page Tobacco sets out what actually works, and how fast the vascular risk comes down.

Signs that mean stopping the pill and seeking care the same day

Drug interactions

A pill can be rendered ineffective by another treatment with no visible sign. The main documented interactions are enzyme inducers: several anti-epileptics (carbamazepine, phenytoin, phenobarbital, primidone, high-dose topiramate), rifampicin and rifabutin, some antiretrovirals, bosentan, modafinil, and St John's wort, an over-the-counter herbal product many people never mention because they do not think of it as a medicine. Ordinary antibiotics, contrary to a persistent belief, do not reduce the pill's effectiveness — rifampicin excepted.

In the other direction, combined contraception alters the levels of other treatments — lamotrigine in particular, whose concentration falls, with a risk of seizures. Tobacco itself speeds the metabolism of several medicines, which is why stopping smoking can require an existing treatment to be adjusted.

The practical rule is one sentence: tell every prescriber you use hormonal contraception, dentist and dermatologist included, and tell the prescriber of the contraception about every supplement and herbal product you take.

The law country by country

The legal framework, the procedure, the time limits and the costs differ from one country to another. Each country below has a detailed page: governing texts, key facts, the actual procedure, costs, where to go and the traps to avoid.

Select a country to open its detailed page.

Europe

Ireland

Free contraception for a wide age band through a national scheme introduced in 2022 and extended since.

Spain

Prescription contraception largely funded by the public health system, IUD and implant fitted free, the emergency pill sold without prescription in pharmacies and free at public centres since 2023; sixteen-year-olds decide alone; condoms freely sold and often free at sexual health centres.

United Kingdom

Free on the NHS for everyone, including condoms at sexual health clinics, with pharmacists now able to supply the pill in England.

Western Africa

Ghana

Provided through public facilities and partly covered by national health insurance, with community compounds serving rural areas.

Nigeria

Free or heavily subsidised, with implants widely available, though stock-outs persist in some states.

Middle Africa

Cameroon

Contraception is legal in Cameroon and part of the national planification familiale (family planning) programmes: the pill, injectables, implants, the IUD and condoms are available in health facilities, pharmacies and family planning associations such as CAMNAFAW, free or subsidised in the public sector; real access remains uneven, and the husband's consent that is sometimes demanded has no legal basis. In the UK contraception is free on the NHS — in England for visitors too — and under-16s can be seen confidentially.

Eastern Africa

Ethiopia

Contraception in Ethiopia is a matter of health policy rather than statute: neither the Criminal Code nor the Revised Family Code mentions it, the Health Sector Transformation Plan (2015/16-2019/20) delivers family planning through health extension workers, and 41% of married women used a modern method in 2019, up from 14% in 2005, with 87% of the methods supplied by the public sector.

Kenya

Free at public facilities and backed by community health workers, with high use of injectables and implants and approved self-injection.

Rwanda

Contraception falls under the family planning services of Law n° 026/2025, which since 18 September 2025 makes 15 the age from which a person consents to health care alone, and 64% of currently married women used a modern method in the 2025 Demographic and Health Survey, against 58% in 2019-20.

Tanzania

Contraception is governed by Ministry of Health guidelines rather than a statute: no parental, guardian or spousal consent is needed (written consent only for permanent methods), public facilities supply methods free, and 31% of married women used a modern method in 2022.

Uganda

Free at government facilities, with village health teams distributing condoms and pills while unmet need among adolescents stays high.

Zambia

Free at public facilities, with implants and injectables the most used methods and community outreach reaching rural districts.

Southern Africa

South Africa

Public services offer a range of contraceptive options. What is available, and the legal rules for young people, need to be checked separately.

Southern Asia

India

Free in the public system, with a long-standing emphasis on sterilisation that is slowly shifting towards spacing methods.

Pakistan

Legal and provided free in the public sector, but uptake is among the lowest in the region.

Eastern Asia

Hong Kong

Inexpensive and easily available through the Family Planning Association and pharmacies.

South-eastern Asia

Indonesia

Everyone has a right of access to family planning services (Health Law 17/2023, art. 63(3)); the 2024 Regulation builds the service around couples of reproductive age and the choice of method without coercion (art. 109), and in 2017 64% of married women used a method, 57% a modern one.

Malaysia

Available through public clinics, NGOs and pharmacies, with the national population board as the main public provider.

Philippines

Free in public facilities under the Reproductive Health Act — but minors generally need parental consent for modern methods.

Singapore

Widely available and inexpensive, but emergency contraception requires a prescription.

Northern America

Canada

Provincial coverage, with British Columbia and others making prescription contraception free, and pharmacist prescribing widespread.

United States

Most insurance must cover contraception with no cost-sharing, and a daily pill is now available over the counter.

Caribbean

Jamaica

Free at public health centres under the National Family Planning Board, with confidential services open to adolescents.

Trinidad and Tobago

Free at public health centres and through the Family Planning Association, with emergency contraception and condoms sold commercially.

South America

Argentina

Contraceptives free in public hospitals and health centres and covered at 100 % by obras sociales (health insurance funds) and prepagas (private health insurers) since 2003; the emergency pill without prescription; tubal ligation and vasectomy from 18 without the spouse's authorisation; adolescents seen alone from 13. Rules close to those of the UK, where contraception is also free — but tied to Argentine cover or the public system, since the NHS pays nothing abroad.

Oceania

Australia

Subsidised through the PBS, with longer dispensing intervals and expanding pharmacist resupply.

New Zealand

Fully funded contraception for most people, with pharmacists able to supply the pill and emergency contraception.

This topic is also covered for French-speaking countries · German-speaking countries · Spanish-speaking countries · Italy and Italian-speaking Switzerland · Portuguese-speaking countries · the Netherlands, Flanders and Suriname · Poland and the Polish diaspora · Türkiye and the Turkish diaspora.

What about you?

In your relationship, contraception is…

Anonymous vote, no account: results appear after you vote, for all readers, readers of the English site and readers in your country. All the results: the polls page.


Sources

  1. Family planning/contraception methods — World Health Organization (WHO), 2025: implants and IUDs are highly effective and long-acting; the condom is the only method that also protects against STIs, including HIV
  2. Contraception and Birth Control Methods — Centers for Disease Control and Prevention (CDC), 2024: typical-use failure rate of each method (implant 0.1%, pill 7%, condom 13%…), IUD durations, internal condom inserted up to 8 hours before
  3. How well contraception works at preventing pregnancy — National Health Service (NHS), 2024: gap between perfect use and typical use: none for implant and IUDs, large for pill and condom
  4. Appendix D: Classifications for Combined Hormonal Contraceptives (U.S. Medical Eligibility Criteria for Contraceptive Use, 2024) — Centers for Disease Control and Prevention (CDC), 2024: combined contraception: smoking after age 35 (category 3 under 15 cigarettes, category 4 above), migraine with aura, rifampicin and antiepileptics, common antibiotics with no effect
  5. Appendix B: Classifications for Intrauterine Devices (U.S. Medical Eligibility Criteria for Contraceptive Use, 2024) — Centers for Disease Control and Prevention (CDC), 2024: the IUD can be used in nulliparous women (category 2, advantages outweigh risks)
  6. Tableau comparatif pour vous guider dans votre choix de contraception — Santé publique France, French national public health agency, accessed 2026 (in French)
  7. Natural family planning (fertility awareness) — National Health Service (NHS), 2024: 2 to 3 cycles to learn the method, taught by a trained practitioner

Official or institutional documents this page relies on, consulted on 12 October 2026. Links open in a new tab.

Content updated in . The instruments cited can change: if in doubt, confirm with the official source given.

Text written with the help of AI, under the editorial responsibility of CAPIT; human reviews are occasional (method and sources: About). This content does not replace medical or legal advice. Spotted an error? Write to us.

Test what you have just read

Five questions, and every answer is somewhere on this page. Nothing is recorded: the score stays in your browser.

A multiple-choice quiz: pick one answer to each question, the correction appears right away and your score at the end.

News

Locate this page in the site map