Four requests that get confused
“I want nice teeth” covers four things with different practitioners, different prices and different funding. Telling them apart before the first appointment stops you paying for a cosmetic procedure where a funded treatment would have done.

- Clean teeth and healthy gums: scaling, treating gingivitis or periodontitis. This is treatment, it is cheap, and it is funded almost everywhere.
- Lighter teeth: whitening. This is cosmetic, funded nowhere, and the price gap between a surgery and an online kit runs from one to twenty.
- Straight teeth: orthodontics. Long, expensive, largely funded for children and rarely for adults.
- Replaced or rebuilt teeth: crown, bridge, denture, implant. This is where the heaviest sums sit, and where national systems diverge most.
The basics, which cost almost nothing
No cosmetic procedure rescues poor hygiene, and the essentials come down to five points everyone knows and few actually apply.

- Two two-minute brushings a day, one of them at night. The night one matters most: saliva, which protects, dries up while you sleep.
- Fluoride toothpaste. The best documented caries prevention there is. Spit, do not rinse: rinsing with water washes away the fluoride you have just applied.
- Clean between the teeth once a day — floss, interdental brushes or a water flosser depending on the gap. A brush does not reach where most adult decay begins.
- A soft brush, not a hard one. Hard brushes and heavy horizontal scrubbing wear the enamel at the neck of the tooth and make the gum recede — two irreversible kinds of damage that then cost a great deal.
- Limit how often you eat sugar, more than how much. Ten sweet snacks through the day do more harm than one dessert: each intake triggers a twenty-minute acid attack. Energy drinks and fizzy drinks add direct acid erosion.
Two quiet enemies: tobacco, which stains, masks bleeding gums and multiplies the risk of periodontitis and implant failure; and bruxism, the night-time grinding that wears teeth down and cracks crowns, and that a simple night guard prevents.
Scaling: the best value treatment there is
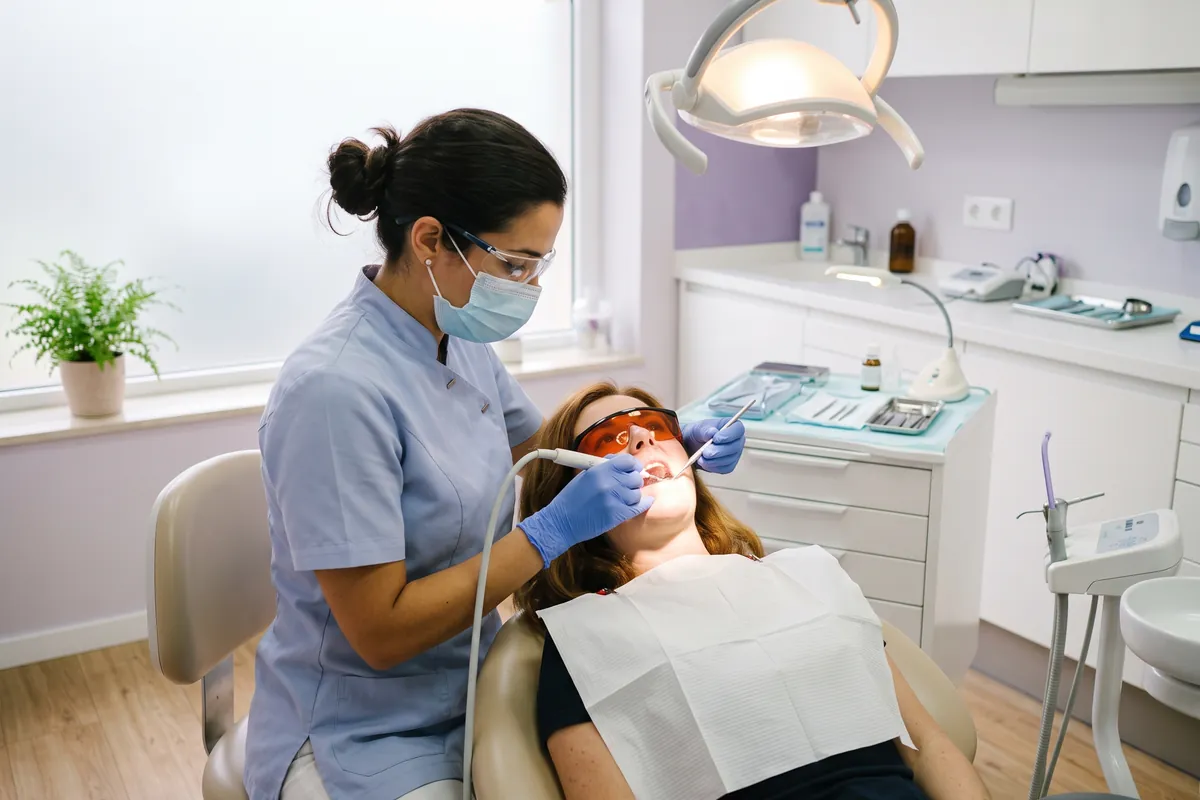
Plaque mineralises into calculus within days, and calculus no longer brushes off. It keeps the gum inflamed — gingivitis, which bleeds and is entirely curable — and that can progress to periodontitis, which destroys the bone holding the tooth and does not repair. Periodontitis is the leading cause of tooth loss after forty, well ahead of decay.
The usual rhythm is one scaling a year, two for heavy calculus formers, smokers, people with diabetes, those wearing braces and during pregnancy — gums react strongly to hormonal change. Bleeding when brushing is never normal: it means go, not brush more gently.
Scaling does not whiten teeth. It removes calculus and surface staining from coffee, tea and tobacco, which often feels like lightening — but the tooth's own shade does not change.
Whitening: what works, what damages
The only effective active is peroxide — hydrogen peroxide, or carbamide peroxide which breaks down into it. Everything else — activated charcoal, bicarbonate, “whitening” toothpastes, coconut oil, lemon — does not lighten the tooth: at best it removes surface staining, at worst it abrades the enamel. Lemon and vinegar are frankly harmful: they dissolve enamel, which does not grow back, leaving the yellower dentine underneath more visible. The result is the opposite of what was wanted.

Three routes exist, and what separates them is the permitted concentration:
- In the surgery, at high concentration, with the gum protected. Fast, in one to three sessions.
- At home in custom-made trays, at lower concentration, over one to three weeks, after an examination and an impression. The best balance of result and safety.
- Over-the-counter products, whose concentration is capped very low in many countries — in the European Union, above 0.1 % hydrogen peroxide a product may only be supplied by a dentist, up to 6 %, with the first application performed in the surgery, and it is prohibited under eighteen. Kits sold online from abroad routinely ignore those limits, and the reported gum burns come almost entirely from there.
What whitening does not do: it has no effect on crowns, composites or veneers, which keep their original shade — hence mismatched teeth if that was not anticipated. It does not correct grey staining from certain childhood antibiotics, nor a darkened root-treated tooth, which need another technique. It is not done over decay or inflamed gums: the prior examination is not a sales formality. Cold sensitivity for a few days is common and passes; the result lasts one to three years depending on coffee, tea, red wine and tobacco.
Straightening crowded teeth

Orthodontics is not only for teenagers: teeth move at any age, and the share of adults treated is rising everywhere. What changes with age is not feasibility but duration, slightly longer, and funding, which almost everywhere stops at an age limit.
- Fixed braces, metal or ceramic: the reference technique, able to correct everything, including rotations and large movements.
- Clear aligners: discreet and removable, effective on mild to moderate corrections provided they are worn twenty-two hours a day. Their limits on complex cases are real.
- Lingual braces, fixed behind the teeth: invisible, more expensive, harder to live with at first.
Aligners sold online without an examination
Several companies sell aligners ordered from a self-taken impression or a shop scan, with no radiograph and no clinical examination. Professional bodies in several countries have warned about this, and regulators have acted against some practices. The problem is not the material, it is the absence of a diagnosis: moving teeth on untreated periodontitis, short roots or an unstable bite causes loosening and tooth loss. A panoramic radiograph and a gum assessment before any movement are not negotiable.
Treatment always ends with a retainer — a wire bonded behind the teeth or a night guard — and it is worn for years, often for life. Relapse after a successful treatment is the main source of disappointment, and it almost always follows an abandoned retainer.
Crowns, bridges, dentures and implants
When a tooth is too broken down to fill, or missing, four solutions coexist. They differ in lifespan, in what they do to neighbouring teeth, and in price.

- A crown covers a tooth that is kept. Ceramic, metal-ceramic, zirconia or metal: the material depends on position — appearance in front, strength at the back — and it drives much of the price and the funding.
- A bridge replaces a missing tooth by resting on the two neighbours, which have to be cut down. That is its major drawback: two healthy teeth damaged to replace one.
- A denture, partial or complete. The cheapest and most widely funded; it needs an adjustment period and regular refitting, as bone resorbs underneath over the years.
- An implant, a titanium screw placed in bone carrying a crown. It leaves the neighbours alone and preserves bone, which is its great advantage; it is also the most expensive, takes months, needs enough bone, and is excluded from funding almost everywhere. Smoking and poorly controlled diabetes clearly raise the failure rate.
Three habits save money: ask for a detailed written quote before any prosthetic work — compulsory in several countries — get a second opinion above a certain amount, and check exactly what your insurance covers, since annual caps are often reached by the second crown.
Going abroad for treatment
This is a large and long-standing practice: Britons to Hungary, French patients to Spain, Portugal or Hungary, Germans to Poland, Hungary or Czechia, Swiss patients to France, Americans to Mexico and Costa Rica, Australians to Thailand. The driver is simple: on heavy work — several implants, a full rehabilitation — the price gap frequently reaches 50 to 70 %, far more than the cost of travelling.

The reasoning holds, on four conditions.
- Get the diagnosis at home first. A panoramic radiograph and a treatment plan drawn up by someone who is not selling the quote give you a basis for comparison. Free foreign treatment plans based on a photograph are a sales tool, not a diagnosis.
- Check what is included. Does the quoted price cover the implant, the abutment and the crown, or only the screw? Any bone graft? The reviews? A three-line quote is not a quote.
- Plan for follow-up and complications. An implant is placed in stages, months apart: count on two or three trips, not one. And ask, in writing, who redoes the work if a crown fractures eight hundred kilometres away — a foreign clinic's guarantee is often limited to repairs carried out on site, at your travel expense.
- Look at what your own country funds. In the European Union, Directive 2011/24/EU on cross-border healthcare allows reimbursement of care received in another member state at the rate of the country of affiliation, after paying up front and, for some procedures, with prior authorisation. That does not make it free, but it changes the arithmetic.
Finally, liability: in a dispute, the applicable law is in principle that of the country where the treatment was given, and litigating there is slow and expensive. That is the real risk of dental tourism — not quality, which is often very good in established clinics, but redress when something goes wrong.
The law country by country
What is funded, what is not and at what price changes completely from one country to the next — this is in fact the field of health where the gaps are widest. Each page gives the reimbursement rates, the caps, the exclusions, the prices actually charged and the low-cost routes.
Select a country to open its detailed page.